
Diabetes is one of the most common chronic conditions in any practice, which makes it one of the highest-volume sources of both revenue and denials. A single patient can generate an office visit, an A1C test, a continuous glucose monitor (CGM) interpretation, education sessions, a retinal screening and a foot exam in the same year, and each service has its own code, its own diagnosis pairing, its own modifier rules and its own frequency limit.
This guide walks through the diabetes CPT codes and matching HCPCS and ICD-10-CM codes that practices bill in 2026. For every service you will find what the code reports, when it applies, the limit or modifier that trips up claims, and the denial fix that protects your revenue. Use it as a working reference for your coders, front desk and billing team.
Is There a CPT Code for Diabetes?
No. There is no single CPT code for diabetes, and this is the first misunderstanding worth clearing up. CPT and HCPCS codes describe the service performed. ICD-10-CM codes describe the diagnosis. Type 2 diabetes without complications is reported with E11.9, but the visit where you managed it, the lab test you ordered and the education you delivered each carry separate procedure codes.
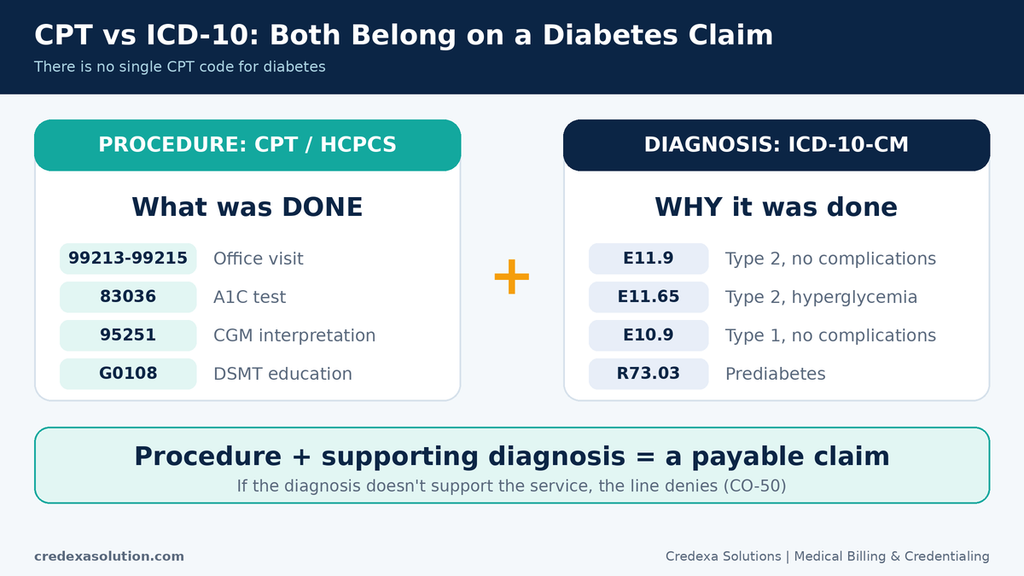
A payable claim needs both halves. The procedure code says what you did, and the diagnosis code proves why it was medically necessary. If the diagnosis does not support the service, the payer has no reason to pay the line.
| What you are reporting | Code set | Example |
|---|---|---|
| Type 2 diabetes, no complications | ICD-10-CM | E11.9 |
| Type 2 diabetes with hyperglycemia | ICD-10-CM | E11.65 |
| Type 2 diabetes in remission | ICD-10-CM | E11.A |
| Type 1 diabetes, no complications | ICD-10-CM | E10.9 |
| Prediabetes | ICD-10-CM | R73.03 |
| Established patient visit | CPT | 99213 to 99215 |
| Hemoglobin A1C test | CPT | 83036 |
| CGM data interpretation | CPT | 95251 |
| Diabetes self-management training | HCPCS Level II | G0108 |
| Home glucose monitor | HCPCS Level II | E0607 |
Accurate diagnosis coding is a skill of its own. Specificity, sequencing and payer edits decide whether a claim survives review, a theme we cover in our hypoxia ICD-10 code guide for 2026, including R09.02 versus J96.01 sequencing and denial prevention. The same discipline applies to diabetes, where the difference between E11.9 and E11.65 can change medical necessity.
Diabetes CPT Codes at a Glance
Most diabetes billing falls into ten service categories. Keep this table handy as a quick reference before we go deeper into each one.
| Service | Primary code | What it covers | Typical limit |
|---|---|---|---|
| Laboratory | 83036 | Hemoglobin A1C | Set by payer policy |
| Office visit | 99213 to 99215 | Established patient E/M | Per encounter |
| CGM interpretation | 95251 | Analysis, interpretation, report | Once per 30 days |
| CGM setup (practice-owned device) | 95250 | Placement, training, removal | Once per month |
| CGM setup (patient-owned device) | 95249 | Startup and training | Once per device |
| Education, individual | G0108 | DSMT per 30 minutes | Annual hour caps |
| Education, group | G0109 | DSMT group per 30 minutes | Annual hour caps |
| Nutrition therapy | 97802 to 97804 | MNT assessment and follow-up | Payer specific |
| Quality reporting | 3044F to 3046F | HbA1c result tiers | Per result |
| Supplies | E0607, A4253 | Meter and test strips | DME policy |
CPT Codes for A1C and Glucose Testing
Laboratory testing is the highest-volume category of diabetes billing, and it is where small coding mistakes repeat across thousands of claims.
83036 vs 83037: Which A1C Code Applies?
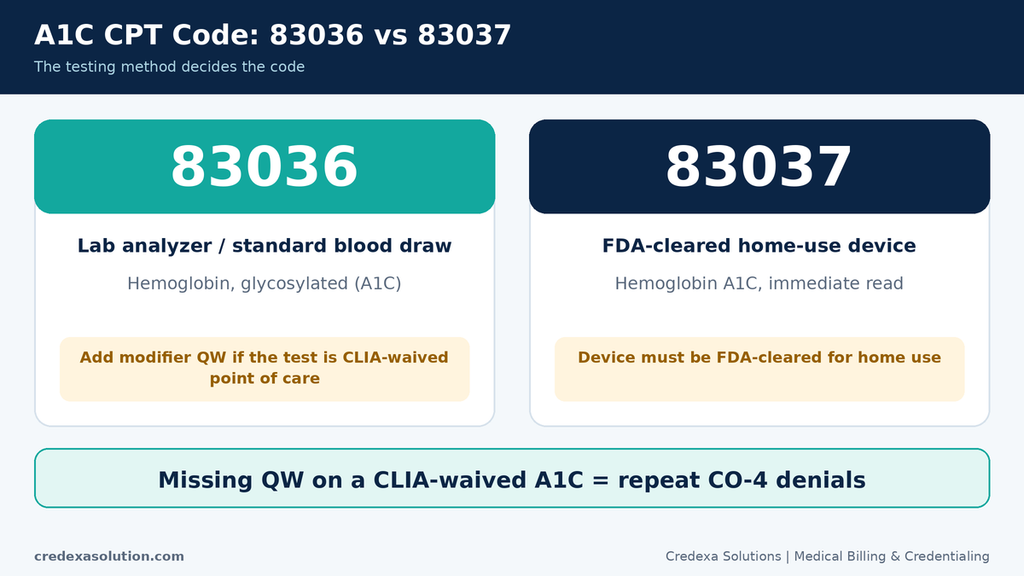
The CPT code for A1C is 83036, which reports hemoglobin, glycosylated (A1C), on a laboratory analyzer or standard blood draw. 83037 reports the same test performed on a device cleared by the FDA for home use with an immediate result. The testing method decides the code.
When the test is performed in your office on a CLIA-waived analyzer, append modifier QW to the line. Missing QW is a classic silent revenue leak: the claim denies, nobody investigates, and the same denial repeats every time that test is billed.
Diabetes Screening vs Monitoring
Screening uses the same lab codes as monitoring, including 82947, 82950, 82951 and 83036. What changes is the diagnosis. Use Z13.1 (encounter for screening for diabetes mellitus) when the purpose is screening. Using a diabetes diagnosis such as E11.9 on a screening claim is a frequent cause of medical necessity denials.
Watch out for outdated references. Some coding pages still list V77.1 and modifier TS for diabetes screening. V77.1 is an ICD-9 code that has been invalid for years, so any resource that recommends it is a signal to check the publication date before trusting the rest of the page.
CGM CPT Codes: 95249, 95250 and 95251
Continuous glucose monitoring carries the most valuable and the most denial-prone diabetes CPT codes. Three professional service codes cover the workflow, and choosing correctly starts with one question: who owns the device?
| Code | Service | Frequency | Face to face |
|---|---|---|---|
| 95249 | Startup and training on a patient-owned CGM | Once per device | Yes |
| 95250 | Practice-supplied CGM placement, training, removal | Once per month | Yes |
| 95251 | Analysis, interpretation and written report | Once per 30 days | No |
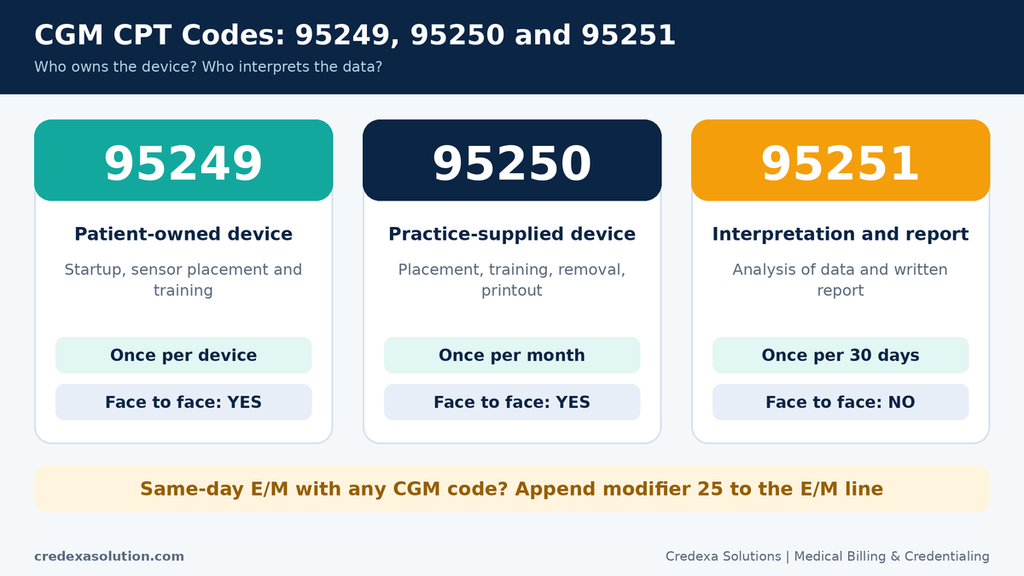
95249 vs 95250: Equipment ownership is the deciding factor. If the patient owns the device and your staff handles startup and training, report 95249. If your practice supplies the equipment for the wear period, report 95250.
95250 vs 95251: 95250 covers the hands-on work of placing the sensor, training the patient and removing the device. 95251 covers reading the data and writing the report. They are separate services, and both can be billed when both are performed.
The Most Common CGM Denials
- Frequency denials on 95251. A second interpretation inside the same 30-day window is denied, and it rarely survives appeal.
- Missing modifier 25. When an E/M visit happens on the same day as a CGM procedure code, append modifier 25 to the E/M line, or the payer bundles the visit into the procedure.
- Weak diagnosis specificity. The diagnosis must support continuous monitoring, not just the presence of diabetes.
- Prior authorization gaps. Authorization obtained after the service, or expired before the date of service, triggers CO-197 denials.
2026 Remote Patient Monitoring Codes for Diabetes
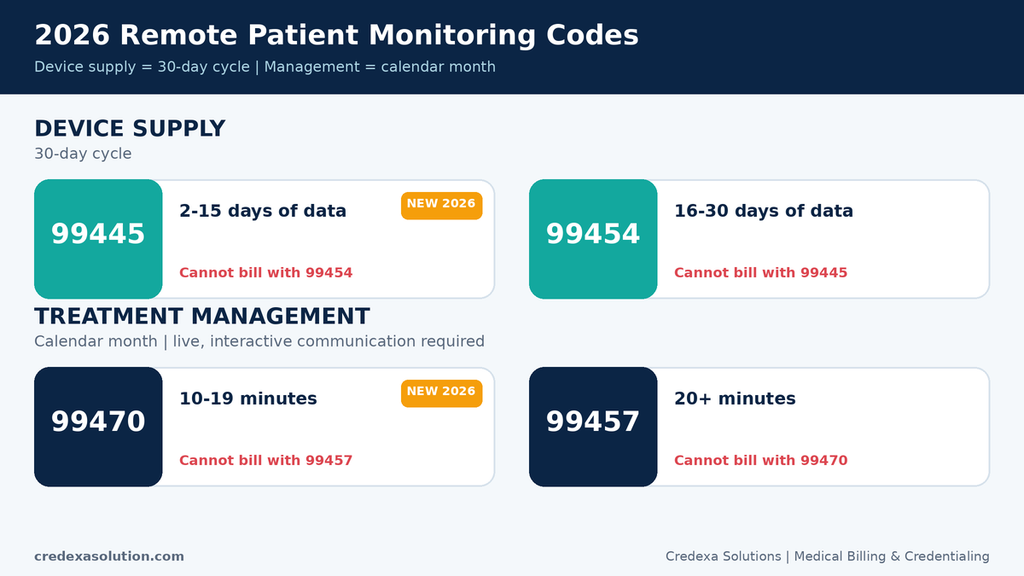
Diabetes programs that use connected glucose devices should pay close attention to remote patient monitoring (RPM). The 2026 Physician Fee Schedule added short-duration RPM codes that close gaps practices previously could not bill for. The CMS CY2026 Physician Fee Schedule final rule fact sheet is the primary source for these changes.
| Code | Threshold | Notes |
|---|---|---|
| 99445 | Device supply, 2 to 15 days of data in 30 days | New for 2026 |
| 99454 | Device supply, 16 to 30 days of data in 30 days | Cannot be billed with 99445 in the same period |
| 99470 | 10 to 19 minutes of management in a calendar month | New for 2026 |
| 99457 | 20 or more minutes of management per month | Cannot be billed with 99470 in the same month |
| 99458 | Each additional 20 minutes | Add-on to 99457 only |
| 99453 | Initial setup and patient education | Once per episode |
Two rules cause most RPM denials. First, the device supply codes run on 30-day cycles while the management codes run on calendar months, and mixing the two clocks produces denials that look inexplicable on the remit. Second, management codes require live, interactive communication with the patient or caregiver. Voicemails and portal messages do not count. For documentation that holds up in an audit, review the Noridian remote physiologic monitoring 2026 updates.
Diabetes Education and Nutrition Codes
Diabetes education is split across several benefits with different codes and different eligible providers, so picking the wrong benefit is an expensive mistake.
| Service | Code | Unit |
|---|---|---|
| DSMT, individual | G0108 | Per 30 minutes |
| DSMT, group | G0109 | Per 30 minutes |
| MNT, initial assessment | 97802 | Per 15 minutes |
| MNT, reassessment | 97803 | Per 15 minutes |
| MNT, group | 97804 | Per 30 minutes |
| MNT, additional hours | G0270, G0271 | Per 15 or 30 minutes |
| Behavioral counseling for obesity | G0447 | Per 15 minutes |
G0108 and G0109: DSMT Rules
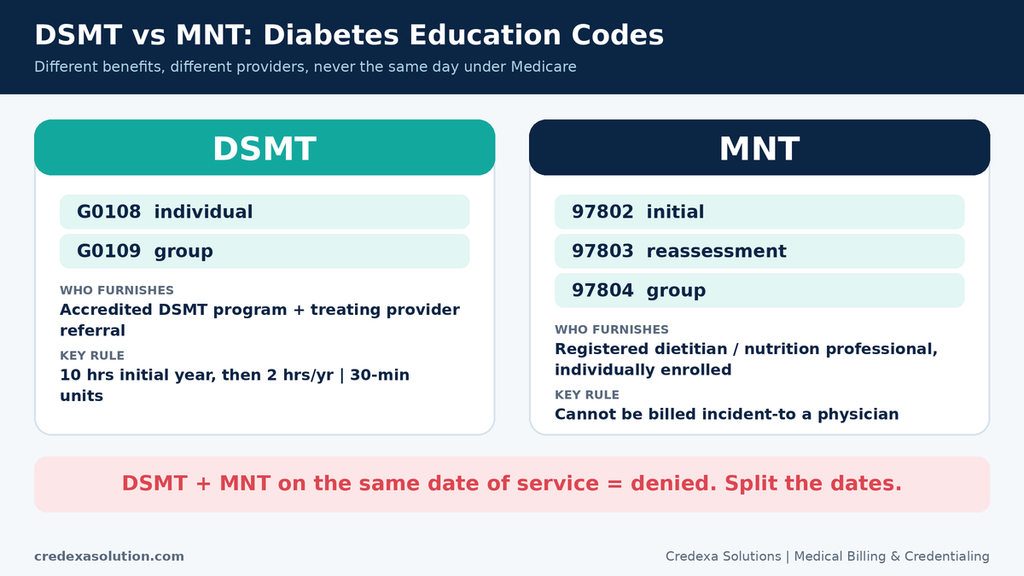
G0108 reports individual diabetes outpatient self-management training in 30-minute units, and G0109 reports the same training delivered to a group. Both require an accredited program and a referral from the treating diabetes provider, along with a documented plan of care. The referral is the most common reason DSMT claims are denied, and it is preventable with eligibility and benefit checks before the visit. The CDC guidance on Medicare DSMES reimbursement explains the referral and increment requirements in detail.
How many hours does Medicare cover? Medicare covers up to 10 hours of initial training within a continuous 12-month period, generally structured as 1 hour individual and 9 hours group. After the initial year, beneficiaries receive 2 hours of follow-up training per calendar year. Because DSMT bills in 30-minute units and partial units do not round up, a 20-minute session generally bills nothing.
MNT Billing Rules
Medical nutrition therapy is billed with 97802, 97803 and 97804, and Medicare pays only when a qualified registered dietitian or nutrition professional furnishes and bills it. It cannot be billed incident to a physician’s services. If your dietitian is not enrolled, the fix is enrollment, not a coding change.
That enrollment step is where many programs stall. Credentialing timelines and portal requirements vary widely by state, and our Wisconsin Medicaid provider enrollment 2026 guide to the ForwardHealth portal shows how a single missed enrollment step can block billing entirely.
Can You Bill DSMT and MNT on the Same Day?
Under Medicare, no. DSMT and MNT furnished on the same date of service are not both payable. Schedule them on separate dates, and confirm the date of service on each claim. Medicare Advantage plans usually follow the Medicare rule, while commercial plans vary, so check each policy.
Category II Codes: Reporting Diabetes Quality Measures
Category II CPT codes carry no payment, but they carry measure credit, and measure credit drives quality bonuses, Star Ratings and value-based contract performance.
| Code | Result reported |
|---|---|
| 3044F | Most recent HbA1c below 7.0% |
| 3051F | Most recent HbA1c 7.0% to below 8.0% |
| 3052F | Most recent HbA1c 8.0% to 9.0% |
| 3046F | Most recent HbA1c above 9.0% |
| 2022F | Dilated retinal exam, retinopathy present |
| 2023F | Dilated retinal exam, no retinopathy |
| 3072F | Low risk for retinopathy |
A practice with excellent glycemic control that never reports these codes looks identical on paper to a practice with poor control. Reporting the result on the claim also saves your team from chart-chase requests months later.
The quality landscape has also shifted toward glycemic status. The NCQA Glycemic Status Assessment for Patients with Diabetes measure accepts a Glucose Management Indicator from CGM data as an alternative to a laboratory HbA1c, connecting your CGM workflow directly to your quality reporting.
Diabetic Eye Exam CPT Codes
There is no single code labeled “diabetic eye exam.” The code you report depends on the exam type and setting.
| Code | Service |
|---|---|
| 92002 to 92014 | Ophthalmological services |
| 99202 to 99215 | Office or outpatient E/M |
| 92227 | Remote retinal imaging, point of care, without physician interpretation |
| 92228 | Remote retinal imaging with remote physician interpretation |
| 92229 | Point-of-care retinal imaging with automated analysis |
92229 is especially valuable in primary care because the automated analysis returns an immediate result. A practice that images the retina in the office can close the eye exam quality gap without depending on an outside referral the patient may never complete.
For medically necessary diabetic eye care, many payers prefer E/M codes over routine 92xxx ophthalmological codes, which can be read as routine vision services. Regardless of the family you choose, the level must match documented medical decision making, and imaging requires a separate interpretation and report.
Diabetic Foot Exam Codes
Medicare ordinarily excludes routine foot care, but patients with diabetic sensory neuropathy and loss of protective sensation (LOPS) are an exception, and three HCPCS codes cover the benefit.
| Code | Service | When to use it |
|---|---|---|
| G0245 | Initial physician evaluation and management | First evaluation by that provider or group |
| G0246 | Follow-up evaluation | Subsequent evaluations |
| G0247 | Routine foot care | Same date of service as G0245 or G0246 only |
G0245 is billed once per beneficiary per provider or provider group. Every later evaluation uses G0246. G0247 is payable only when it appears on the same date as G0245 or G0246. Submit it on its own date and it denies regardless of documentation quality. Medicare generally covers the evaluation no more often than every six months, provided the patient has not seen another foot care specialist for another reason in that interval.
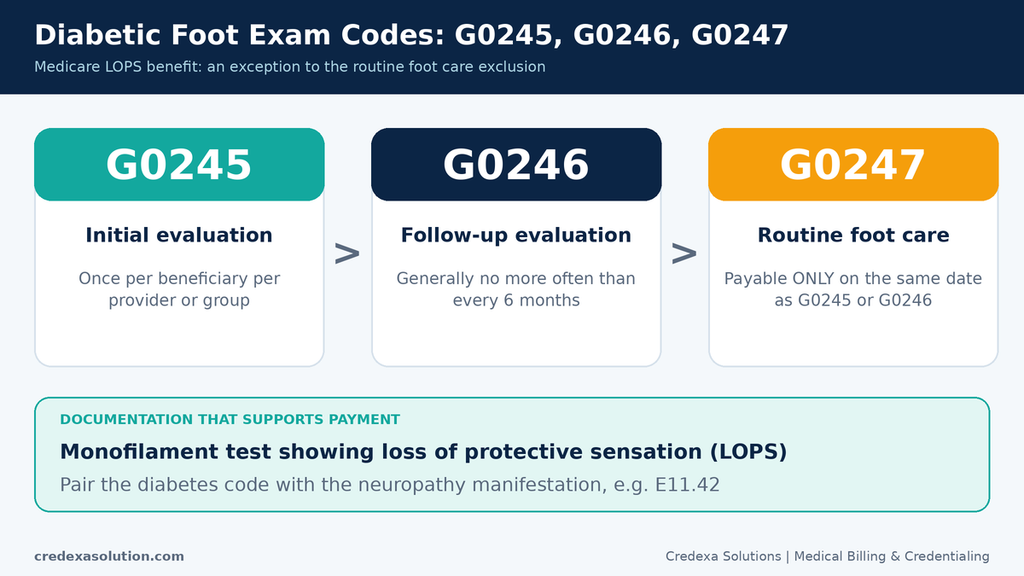
Documentation: LOPS must be documented, not assumed from the diabetes diagnosis. Monofilament testing is the standard, and the claim should pair the diabetes code with the neuropathy manifestation, such as E11.42 for diabetic polyneuropathy.
Diabetes Supply and DME HCPCS Codes
Supplies are billed under HCPCS Level II, not CPT, and the CGM code set changed on January 1, 2023.
| Code | Description |
|---|---|
| E2103 | Non-adjunctive CGM receiver/monitor (current) |
| A4239 | Monthly CGM supply allowance, non-adjunctive (current) |
| K0554 / K0553 | Legacy CGM codes, no longer valid for current dates of service |
| E0607 | Home blood glucose monitor |
| A4253 | Test strips, 50 per box |
Submitting a legacy K-code on a current claim produces a denial that looks like a coverage problem but is really a code-set problem. CGM lines may also require modifiers such as CG and KF depending on device and coverage criteria. The CMS Glucose Monitor policy article A52464 documents the transition, the modifier rules and the covered diagnoses. Prior authorization and expired approvals cause more DME denials than coding errors, so secure and track authorizations before the device ships.
E/M Coding for Diabetes Visits
A diabetes diagnosis does not set the E/M level. Medical decision making (MDM) or total time on the date of the encounter does.
- 99213: A stable patient at goal with no medication changes (one stable chronic illness, low risk).
- 99214: A patient with a rising A1C whose insulin is started or adjusted (chronic illness with progression plus prescription drug management).
- 99215: Multiple uncontrolled conditions or a decision regarding hospitalization.
Two add-on opportunities are frequently missed. Chronic care management (99490, 99491, 99487) can be billed when a patient has two or more chronic conditions, and diabetes commonly pairs with hypertension, kidney disease and hyperlipidemia. G2211, the visit complexity add-on for longitudinal care, fits ongoing diabetes management when the same provider manages the condition over time.
For virtual visits, verify current telehealth status and place of service before billing. The Telehealth.HHS.gov diabetes billing guide and the CMS telehealth FAQ are the best places to confirm what remains payable.
Pairing Diabetes ICD-10-CM Codes Correctly
Diabetes diagnoses fall into these categories:
- E08: Diabetes due to an underlying condition
- E09: Drug or chemical induced diabetes
- E10: Type 1 diabetes
- E11: Type 2 diabetes (the default when type is not documented)
- E13: Other specified diabetes
- O24.4: Gestational diabetes
Key Coding Rules
“With” convention: The ICD-10-CM index presumes a causal link between diabetes and certain conditions listed under “with,” such as chronic kidney disease, so they are linked when both are documented. The FY2026 ICD-10-CM official guidelines set this rule.
Uncontrolled diabetes: There is no default code for “uncontrolled.” Documentation of “poorly controlled” or “out of control” generally codes to hyperglycemia (E11.65 or E10.65), but if the note describes hypoglycemia, the code changes, so read the documentation carefully.
E11.A (remission): This code reports type 2 diabetes without complications, in remission, and requires the provider to document remission. “Resolved” is not the same as “in remission,” and a coder who sees “resolved” should query the provider.
Insulin status: Z79.4 is not reported with type 1 diabetes because insulin dependence is assumed. Report it with type 2 diabetes for long-term insulin use. Use Z79.84 for oral hypoglycemics and Z79.85 for injectable non-insulin drugs such as GLP-1 receptor agonists.
Type 1 and type 2 together: An Excludes1 note prevents reporting E10 and E11 together unless the provider documents that the conditions are unrelated. Otherwise, query the provider.
Essential Modifiers for Diabetes Claims
| Modifier | Meaning | Applies to |
|---|---|---|
| 25 | Significant, separately identifiable E/M on the same day as a procedure | The E/M code |
| QW | CLIA-waived test | 83036 and other waived tests |
| 26 / TC | Professional or technical component | Diagnostic services with a split |
| 59 / XU | Distinct procedural service | Column two code of an NCCI pair |
| KX | Coverage criteria met | DME claims |
| CG, KF | CGM criteria met, Class III device | CGM DME lines |
| JW / JZ | Drug discarded / no drug discarded | Injectable drug claims |
Modifier 25 deserves special attention. It must be supported by documentation of work beyond what the procedure already includes. It does not manufacture a separate service. Unbundling rules are governed by NCCI edits, which change quarterly, so review the CMS NCCI FAQ library regularly.
Bundling and unbundling logic is not unique to diabetes. It appears in every specialty where procedures and visits share a claim, including urology. Our lithotripsy CPT codes 2026 guide covering billing, reimbursement and denial prevention is a useful companion for understanding how facility and professional coding interact with denial edits.
Codes That Cannot Be Billed Together
| Pair | Why it fails | Fix |
|---|---|---|
| 99445 and 99454 | Mutually exclusive supply tiers | Bill the tier that matches transmission days |
| 99470 and 99457 | Mutually exclusive time tiers | Bill the tier that matches documented time |
| DSMT and MNT, same day | Medicare will not pay both | Separate the dates of service |
| E/M plus 95249/95250/95251 without 25 | Visit bundled into procedure | Append modifier 25 |
| G0247 without G0245/G0246 | Payable only with an evaluation | Bill on the same date |
Why Diabetes Claims Get Denied
| Denial code | Meaning | Typical diabetes cause |
|---|---|---|
| CO-50 | Not medically necessary | Diagnosis does not support the service |
| CO-97 | Included in another service | Same-day E/M without modifier 25 |
| CO-197 | Authorization missing or invalid | CGM or pump authorization lapsed |
| CO-16 | Missing information | Missing modifier, credential or documentation |
| CO-4 | Modifier inconsistent | QW missing on CLIA-waived A1C |
| CO-151 | Units exceed limit | Second 95251 within 30 days |
| CO-234 | Not separately payable | Service included in another billed service |

Six Checks Before You Appeal
- Does the diagnosis on the claim support the specific service billed?
- Was this code already billed inside its frequency window?
- Was an E/M billed the same day as a procedure, and does it carry modifier 25?
- Was a required modifier missing (QW, KX, CG, KF, JW or JZ)?
- Was prior authorization active on the date of service?
- Does the note document what the code requires, such as time, transmission method or interpretation?
Most denied diabetes claims fail at least one of these checks, and finding the cause takes far less time than writing an appeal letter. Also watch your filing windows. A claim that ages in a queue past the timely filing limit is no longer appealable, and that is a workflow failure rather than a payer decision.
Frequently Asked Questions About Diabetes CPT Codes
What is the CPT code for an A1C test?
The CPT code for A1C is 83036 for laboratory analysis. Use 83037 for FDA-cleared home-use devices with an immediate read, and append QW for CLIA-waived tests.
What are the CPT codes for continuous glucose monitoring?
The CGM professional codes are 95249 (patient-owned device startup), 95250 (practice-supplied device) and 95251 (interpretation and report).
How often can 95251 be billed?
Generally once per 30 days. A second interpretation in the same window commonly produces a frequency denial.
What is the CPT code for diabetes education?
G0108 covers individual diabetes self-management training and G0109 covers group sessions, both in 30-minute units and both requiring an accredited program and referral.
What is the code for a diabetic foot exam?
G0245 reports the initial evaluation, G0246 reports follow-up evaluations, and G0247 reports routine foot care on the same date as either.
What is the ICD-10 code for type 2 diabetes?
E11.9 reports type 2 diabetes without complications. Use E11.65 for hyperglycemia and E11.A when the provider documents remission.
Can DSMT and MNT be billed on the same day?
Not under Medicare. Schedule them on separate dates of service.
What is new for diabetes billing in 2026?
CPT added short-duration remote monitoring codes 99445 and 99470, and E11.A became available for type 2 diabetes in remission under the FY2026 ICD-10-CM update.
How Credexa Solutions Helps With Diabetes Medical Billing
Knowing the diabetes CPT codes is the easy part. Keeping every claim clean across frequency limits, modifiers, authorizations, payer policies and enrollment requirements is where practices lose time and money. That is where Credexa Solutions steps in as your billing and credentialing partner.
Here is how Credexa Solutions supports your diabetes billing and revenue cycle:
- Coding accuracy and claim scrubbing. Every claim is reviewed for diagnosis-to-procedure alignment, required modifiers such as 25, QW, CG and KF, and code-set currency, so legacy or mismatched codes never reach the payer.
- Frequency and eligibility tracking. We monitor 30-day and monthly limits for CGM, DSMT hour caps and foot exam intervals, and verify eligibility and referrals before the service is delivered.
- Prior authorization support. CGM, pump and DME approvals are secured before the date of service and tracked so they never expire mid-therapy.
- Denial management and root-cause fixes. We work CO-50, CO-97, CO-197, CO-16, CO-4 and CO-151 denials, then trace each one back to the workflow step that created it so the same denial stops repeating.
- Provider enrollment and credentialing. Dietitians, DSMT programs, DME suppliers and new providers must be enrolled before any claim can pay, and Credexa Solutions handles payer and Medicaid enrollment from application through approval.
- Accounts receivable follow-up. Aging claims are worked by value and filing deadline so nothing expires unworked.
- Transparent reporting. You see first-pass acceptance, denial trends and collections in clear reports, so you can measure the impact.
Whether you run a primary care panel, an endocrinology practice, a podiatry clinic or a multi-specialty group, a partner who handles the coding detail lets your clinicians focus on patients rather than payer rules.

Ready to stop losing revenue on diabetes claims? Visit Credexa Solutions to request a billing review and see where your claims are leaking revenue. Credexa Solutions can help you code accurately, get paid faster and stay compliant in 2026 and beyond.
Disclaimer: Codes, payer policies and frequency limits change frequently. Always verify against current CPT, HCPCS, ICD-10-CM and payer-specific guidance before submitting claims.